
You finally book the crown your dentist has been nagging you about for two years, figuring that now you have Medicare, it’s covered. Then the office hands you the bill for the full amount, because Medicare doesn’t pay a cent toward it.
That surprise catches a lot of new retirees off guard, and it isn’t limited to teeth. Original Medicare pays for hospital stays, surgeries, and doctor visits, but it draws a hard line around the everyday care most people over 65 actually need: dental work, glasses, hearing aids, and the custodial help that keeps someone in their own home or a nursing facility.
None of that changes heading into 2027. If anything, the price tags on these services keep climbing, and the fall enrollment window that opens October 15 is the one chance most people get each year to plan around what Medicare leaves out instead of discovering it at the worst possible moment.
Table of contents
- Routine dental care
- Routine vision care and eyeglasses
- Hearing aids and the exams to fit them
- Long-term custodial care
- Elective cosmetic procedures
- Most alternative therapies
- Care you get outside the U.S.
- How Medicare Advantage bundles some of this back in
- What Medigap actually does here
- Standalone policies, long-term care insurance, and Medicaid
- Deciding what matters most before December 7
Routine dental care

Original Medicare treats teeth like they belong to someone else’s body. Cleanings, fillings, tooth extractions, and items like dentures and implants all fall outside Part A and Part B, no matter how badly you need the work. A routine cleaning runs $75 to $200, and a single filling costs $100 to $400. Pulling a tooth can run $150 to $400 for a simple extraction, more if it’s surgical, and a full set of dentures starts around $1,000 and climbs past $3,000 before implants enter the picture.
There is one narrow opening. Medicare will pay for dental work when it’s directly tied to a covered medical treatment, like an oral exam before a heart valve replacement or an organ transplant, or clearing an infection before cancer treatment. Outside those specific circumstances, you’re covering the dentist yourself, and most people over 65 eventually need some kind of dental work.
Routine vision care and eyeglasses
The same logic applies to your eyes. Medicare doesn’t cover eye exams for eyeglasses or contact lenses, and you pay 100% of the cost yourself. A comprehensive exam runs roughly $50 to $300, with a national median around $150, and that’s before you buy frames and lenses, which run a median of $184 at a warehouse club and closer to $400 at an independent eyewear shop.
Cataract surgery is the exception worth knowing about. It’s one of the most common procedures performed on people over 65, and Medicare covers it along with one pair of eyeglasses with standard frames, or one set of contact lenses, after each cataract surgery that implants an intraocular lens. You still pay 20% of the approved amount after your deductible, but that’s a very different bill than paying for glasses on your own. Medicare Part B also covers an annual diabetic eye exam and glaucoma screening for people at high risk. Everything else, including a new prescription because your eyes have simply changed with age, is on you.
Hearing aids and the exams to fit them

Medicare doesn’t cover hearing aids or the exams needed to fit them, and you pay all of the cost. That’s a real number to plan around. A recent survey of more than a thousand buyers found the average price paid for a pair of prescription hearing aids was $2,694, with premium technology running as high as $8,500. Over-the-counter models bought without a clinic visit cost far less, but they’re built for milder hearing loss, not the more significant loss that shows up more often with age.
Medicare will pay for a diagnostic hearing or balance exam if your doctor orders one to investigate a medical condition, such as sudden hearing loss or dizziness, and you’ll owe your usual Part B coinsurance for that visit. What Medicare won’t do is pay for the exam that fits you for a device, or for the device itself. If hearing loss runs in your family or you’re already noticing it, that’s a cost worth budgeting for well before you need the aids.
Long-term custodial care

Long-term custodial care causes more financial damage than any other exclusion on Medicare’s list, and it surprises people because Medicare does pay for some nursing home care, just not the kind most families actually need. Medicare Part A covers up to 100 days in a skilled nursing facility after a qualifying hospital stay: nothing for the first 20 days beyond your Part A deductible, a daily copay of $217 for days 21 through 100, and everything after that is yours. That coverage is for skilled, medically necessary care, not for help with daily living.
Custodial care, help with dressing, bathing, and other everyday tasks, isn’t covered by Medicare at all, whether it happens at home or in a nursing home. And the price of that care keeps rising: the national median cost of a nursing home now runs $9,581 a month for a semi-private room and $10,798 a month for a private one. Most families who end up needing this level of care for any length of time eventually turn to Medicaid, which is now the primary payer for 63% of nursing home residents nationwide, but only after a person’s own savings are largely spent down.
Elective cosmetic procedures
Medicare doesn’t cover most cosmetic surgery unless it’s needed because of an accidental injury or to improve the function of a malformed body part, and you pay 100% of the cost for anything that doesn’t meet that bar. Breast reconstruction after a mastectomy is a specific, covered exception, treated as reconstructive rather than cosmetic.
Some procedures live in a gray area and require prior authorization before Medicare will consider paying, including eyelid surgery to remove excess tissue, Botox injections for muscle disorders, skin removal surgery on the abdomen, rhinoplasty, and vein ablation. Medicare reviews these case by case to decide whether the procedure is treating a real medical problem or simply changing how you look, and the same operation can land on either side of that line depending on why it’s being done. If your provider recommends something in this category, ask directly whether it needs prior authorization and what happens to the bill if that request gets denied, because the answer changes what you owe by thousands of dollars.
Most alternative therapies
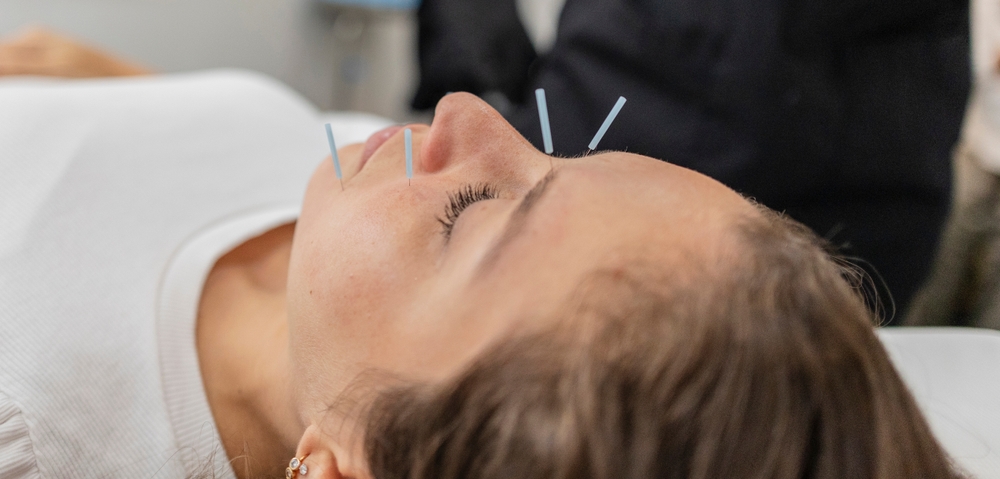
Medicare’s approach to alternative medicine is narrow and specific rather than broad. The one real exception is acupuncture, and only for one condition: Medicare Part B covers up to 12 acupuncture sessions in 90 days for chronic low back pain, with 8 additional sessions if you’re improving, and only when performed by a qualified provider. The back pain has to meet a specific clinical definition, lasting 12 weeks or longer with no identifiable cause tied to surgery or pregnancy.
Everything else in this category, massage therapy, homeopathy, naturopathy, and most chiropractic care beyond medically necessary spinal manipulation, stays outside Medicare entirely, regardless of how many doctors recommend it or how well it might work for you. That’s a program-wide rule rather than a judgment call your own doctor can override, so appealing a denial for a therapy Medicare has already excluded rarely goes anywhere. If alternative therapies are a regular part of how you manage a chronic condition, that’s a cost to plan for separately rather than an expense you can expect Medicare to absorb.
Care you get outside the U.S.

Retirement often comes with more travel, and this is where Medicare’s limits catch people by surprise. Medicare usually doesn’t cover health care while you’re traveling outside the U.S., and you pay all costs in most cases. There are three narrow exceptions built around genuine emergencies and geography, such as living so close to the border that a foreign hospital is actually nearer than the closest U.S. facility, but they don’t apply to routine or planned care of any kind.
A Medigap policy can cover part of that cost. Most Medigap plans, lettered C, D, F, G, M, and N, cover 80% of billed charges for certain medically necessary emergency care outside the U.S., subject to a deductible and a lifetime limit of $50,000. Without that kind of policy, or a separate travel medical insurance plan, an emergency hospitalization overseas comes entirely out of your own pocket, and foreign hospitals aren’t required to bill Medicare directly on your behalf, so you may need to pay upfront and file for reimbursement yourself.
How Medicare Advantage bundles some of this back in

Medicare Advantage plans are where most of these exclusions get patched over, at least on paper. Virtually every plan advertises something in this space: 98% or more of individual Medicare Advantage plans offer some vision, dental, or hearing benefit in 2026, and three quarters of enrollees pay no premium beyond the standard Part B premium. For someone weighing the seven exclusions above, that combination looks appealing on its face: one plan, no extra monthly cost, and a benefit that at least touches every category.
The benefit exists, but the fine print decides how much it actually helps. Annual dental maximums commonly land between $1,000 and $2,000, provider networks can be narrow, and the plan’s overall out-of-pocket limit still matters: the average in-network out-of-pocket limit across Medicare Advantage plans is $5,421. Before you assume a plan solves your dental or hearing needs, pull up its actual benefit summary and check the annual cap and the provider list, not just whether the category is listed on a brochure.
What Medigap actually does here

Medigap is built to solve a different problem than the one you’re weighing here, and it’s worth being clear-eyed about that before you buy one expecting it to cover dental work or a hearing aid. Medigap policies help cover your copayments, coinsurance, and deductibles for services Original Medicare already covers, which lowers your costs on things like hospital stays and skilled nursing coinsurance.
What it doesn’t do is add coverage Medicare never had in the first place. Medigap plans generally don’t cover long-term care, vision or dental care, hearing aids, glasses, or private-duty nursing. If you’re choosing between a Medigap policy and a Medicare Advantage plan, understand what each one is actually solving: Medigap reduces your share of the medical bills Medicare already pays for, while Medicare Advantage is more likely to include some benefit toward the categories Medicare excludes entirely, with its own trade-offs in network size and annual limits.
Standalone policies, long-term care insurance, and Medicaid

For the costs neither Original Medicare nor a Medigap policy will touch, a handful of separate options exist, each with its own cost and its own limits. A standalone dental plan for someone over 65 typically runs $20 to $70 a month, and similar standalone policies exist for vision and hearing, usually with their own annual maximums and waiting periods for major work.
Long-term care insurance covers custodial care directly, but the premium climbs steeply the longer you wait to buy it. Annual premiums for a policy bought at 55 run roughly $950 to $1,500, rising to $1,200 to $1,900 by 60 and considerably higher after that, with women generally paying more than men. For people who can’t afford that kind of policy or who need custodial care without having planned for it, Medicaid covers long-term nursing home care once income and assets fall under strict state limits, generally around $2,982 a month in income and $2,000 in countable assets for a single applicant in 2026. Getting there usually means spending down savings first, and Medicaid reviews the prior 60 months of financial records to check for asset transfers.
Deciding what matters most before December 7

Fall open enrollment isn’t just a chance to shop for a lower premium. It’s the one structured moment each year to look honestly at which of these exclusions actually apply to your situation and choose coverage accordingly. The Annual Enrollment Period runs October 15 through December 7, 2026, and any changes you make take effect January 1, 2027.
If your teeth and eyes are in decent shape but you’re already noticing hearing loss, a plan with a strong hearing benefit and a weak dental one might be the better trade. If long-term custodial care is the bigger worry, given a family history or your own health, that points toward long-term care insurance or an honest look at your Medicaid eligibility timeline rather than anything Medicare Advantage or Medigap will solve. There’s no single plan that covers every exclusion on this list, so the useful question isn’t which plan covers everything. It’s which two or three of these exclusions would actually hurt you the most, and which coverage handles those.
None of these exclusions are new for 2027, and none of them are likely to disappear anytime soon. Knowing exactly where they sit, and what they cost, is what turns a surprise bill into a decision you already made.











